Introduction
A plain (survey) radiograph often cannot separate one soft tissue organ from the next. A contrast study adds a material that changes how many x-rays an organ absorbs, so its lumen, lining or vessels stand out.2 Ultrasound, endoscopy, CT and MRI have replaced many of these studies, but they are still the best test in some cases and can be done in most practices with ordinary equipment.2
The technician usually prepares the patient, draws up and gives the agent, times and takes the series of radiographs, and watches for reactions. The veterinarian chooses the study and reads it. This guide covers positive, negative and double contrast, barium versus iodinated agents, the common studies, patient preparation and adverse reactions.
Key facts
- Positive contrast agents are radiopaque (white on the image): barium sulfate for the GI tract and iodine-based agents for vessels, the urinary tract and the spinal canal.2
- Negative contrast is a gas. Double contrast uses a small amount of positive agent to coat the lining, then gas to distend the lumen.1
- Barium is contraindicated when GI perforation is suspected. Use a water-soluble iodinated agent instead, because leaked barium worsens peritonitis and causes a granulomatous reaction.15
- Always take survey radiographs before giving any contrast agent.1
- Upper GI series: withhold food 18 to 24 hours, give about 10 mL/kg barium, and take views immediately and at 20 to 30 minutes, 1 hour and 2 hours.1
- Excretory urography phases, in order: arteriogram, nephrogram, pyelogram, cystogram.1
- Myelography uses a nonionic iodinated agent such as iohexol, about 0.3 to 0.45 mL/kg, with a total volume no higher than 8 mL even in giant dogs.4
- Nonionic, low-osmolar agents have almost completely replaced ionic agents for IV use because they cause fewer hemodynamic reactions.2
How the VTNE tests this
- Choose the agent: barium or iodinated, ionic or nonionic, room air or carbon dioxide. Domain 6 Task B (produce and document diagnostic images following protocols for safety and quality); K39 (diagnostic imaging equipment and procedures, including contrast studies).6
- Prepare the patient: fasting times, enemas, survey films, removing leashes from the neck.
- Put things in order: the timing of an upper GI series or the phases of an excretory urogram.
- Spot the danger: suspected perforation, aspiration risk, air embolism with room air, post-myelogram seizures.
- Calculate: a contrast volume from a dose in mL/kg, and check it against a maximum.
Core concepts
Positive, negative and double contrast
Positive contrast media absorb more x-rays than soft tissue, so they look white (radiopaque). Barium sulfate is given by mouth or rectum to outline the lumen and mucosa (lining) of the GI tract. Iodinated agents given IV make blood vessels visible and are cleared mainly by the kidneys, which then outlines the urinary collecting system. Iodinated agents are also used intrathecally (into the space around the spinal cord).2
Negative contrast media are gases. They absorb fewer x-rays and look black (radiolucent). In a pneumocystogram, gas fills the bladder so that material inside the lumen is not hidden by urine or positive contrast.1
Double contrast combines the two in one patient. A small volume of positive agent coats the lining and gas distends the organ, which shows mucosal detail. Examples are the double-contrast cystogram and a barium enema followed by air.1
Barium sulfate versus iodinated agents
Barium gives excellent mucosal coating, but it is not absorbed. If it leaks into the abdomen it worsens peritonitis. Barium peritonitis can lead to shock, sepsis, granulomas and adhesions, and the prognosis is guarded to poor.5 Leaked barium in the neck or mediastinum also causes a granulomatous reaction.3 Barium is also avoided when the lower bowel may be obstructed, because it can add to the obstipation.1
Water-soluble iodinated agents are the choice when perforation is suspected.1 Oral diatrizoate (an ionic agent) is hypertonic, so it is diluted one part agent to two parts water.1 For a suspected pharyngeal or esophageal tear, a nonionic iodinated agent diluted 50:50 with sterile water can be used.3 Iodinated agents are not mixed with kibble, because food leaking through a tear is undesirable.3
| Agent | Type | Main routes and studies | Key caution |
|---|---|---|---|
| Barium sulfate | Positive | Oral or rectal: esophagram, upper GI, barium enema | Not with suspected perforation; postpone with severe aspiration pneumonia |
| Ionic iodinated (for example diatrizoate) | Positive, water-soluble | Oral GI study when perforation is suspected; older IV agents | Hypertonic: dilute 1:2 with water for oral use |
| Nonionic iodinated (for example iohexol) | Positive, water-soluble, low osmolar | IV urography, urethrogram, cystogram, myelogram | Watch for hypotension and anaphylaxis after IV use |
| Carbon dioxide or nitrous oxide | Negative (gas) | Pneumocystogram, double-contrast studies | Preferred over room air: dissolves in blood |
| Room air | Negative (gas) | Pneumocystogram, after barium enema | Risk of fatal venous air embolism, worst with hematuria |
Sources: Kirk and Bistner's Handbook (ref 1); Merck Veterinary Manual (ref 2); Pollard 2012 (ref 3).
Adverse reactions to IV iodinated contrast
Contrast media have very low toxicity, but IV agents cause known blood pressure changes: a reflex drop in blood pressure followed by a mild rebound rise. In extreme cases the drop leads to vascular collapse. Anaphylaxis and acute kidney failure have also been reported. These effects are linked mainly to hypertonic ionic agents and are much less common with nonionic agents.2 The technician keeps the IV catheter patent, monitors pulse, blood pressure and mucous membranes during and after the injection, and tells the veterinarian at once about vomiting, swelling or hives.
Procedure or technique
Every study starts the same way: confirm the order and the agent with the veterinarian, check the patient is prepared, clean any dirt or debris from the hair coat, and take survey radiographs.1 Survey films show whether the bowel is clean, confirm the technique is right, and sometimes answer the question without contrast.
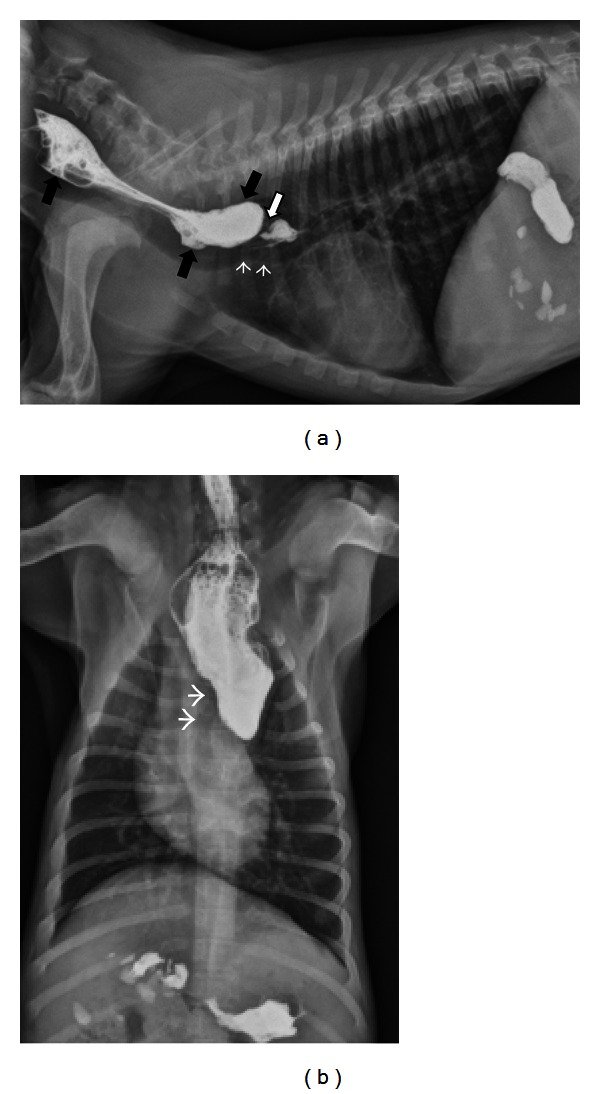
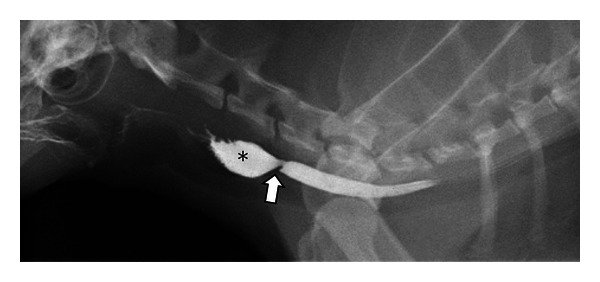
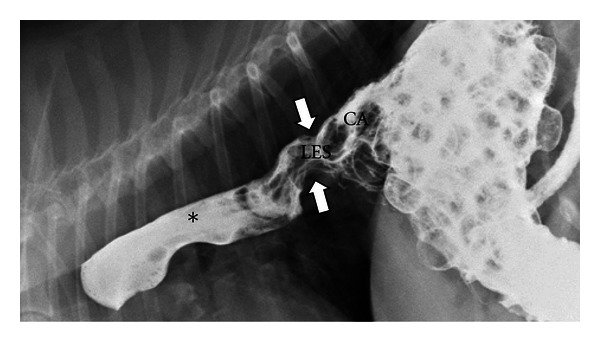
Contrast esophagram (barium swallow)
- Fast the patient 12 hours. Remove all leashes from around the neck, then take survey thoracic radiographs.1
- Give barium suspension, 2 to 5 mL/kg. A thick, paste-like barium coats the esophagus well. Give about a tablespoon by mouth and expose on the second swallow.1
- Take lateral, ventrodorsal (VD) and right ventrodorsal oblique views of the thorax.1
- For a suspected partial stricture, the veterinarian may have the patient eat kibble mixed with barium, because liquid can pass a stricture that food cannot.1
Fluoroscopy (real-time x-ray video) is ideal because it shows swallowing and esophageal motility as they happen.1 For a fluoroscopic swallow study, liquid barium is given in small 5 to 10 mL boluses by catheter-tipped syringe and at least three swallows are watched.3 Patients with swallowing disorders can aspirate regurgitated contrast, and sedation raises that risk.1
Upper GI series (stomach and small intestine)
- Withhold food 18 to 24 hours. If the colon is full of feces, give a cleansing enema the evening before. In dogs a second enema is given 3 to 5 hours before the series.1
- Take survey abdominal radiographs.1
- Give micropulverized barium sulfate, about 10 mL/kg, by stomach tube or by letting the patient swallow.1
- Immediately: VD, right lateral and left lateral views. The right lateral shows barium in the pylorus; the left lateral shows the cardia and fundus.1
- At 20 to 30 minutes, 60 minutes and 2 hours: VD and right lateral views. Label every image with the time after dosing so the veterinarian can judge transit.1
Normal guidelines: barium reaches the duodenum within 15 minutes in most patients (excitement can delay this to 20 to 25 minutes), the jejunum by 30 minutes, the ileocecal junction by 90 to 120 minutes, and has cleared the upper GI tract by 3 to 5 hours. The colon is usually filled by 6 hours and may hold barium for 2 to 3 days.1 Water-soluble agents move faster, passing through the GI tract in 30 to 90 minutes, compared with 60 to 180 minutes for barium.1
Barium enema
Give a liquid diet for 24 hours and cleansing enemas beforehand, but no irritating enemas within 12 hours of the study. Place a cuffed rectal catheter with the inflated bulb cranial to the anal sphincter, with the patient in right lateral recumbency. Infuse 15% to 20% w/v barium by gravity at 20 to 30 mL/kg, never under pressure, with the bag no more than 18 inches above the patient. Radiograph after two thirds of the dose. Then drain the barium and infuse room air at 2 mL/kg for a double-contrast view. Do not overdistend the colon.1 Ultrasound or colonoscopy is now preferred for most of these questions.1
Excretory urography (IV urogram)
Fast 12 to 18 hours, give a cleansing enema or saline laxative 12 to 18 hours before, empty the bladder just before the study, place an IV catheter, and take survey radiographs. The veterinarian gives an iodinated agent at 850 mg/kg of an iodine compound as a continuous IV push. Take a VD view at 10 seconds, then VD and lateral views at 1, 3, 5, 15, 20 and 40 minutes.1 The study shows anatomy, not quantitative kidney function, so it does not replace kidney function tests.1
Retrograde urethrogram and cystogram
A urethrogram injects aqueous iodinated contrast into the urethra through a balloon-tipped catheter. The agent can be mixed with sterile lubricating jelly (three- to fivefold dilution) to thicken it, or diluted 1:3 with sterile water or saline. Give a cleansing enema first. Inject 5 to 10 mL and take the lateral view near the end of the injection while the urethra is still under pressure. In a male dog the catheter tip sits distal to the os penis.1
Cystography can be positive (organic iodides at 5% to 10%), negative (pneumocystogram) or double contrast. For a pneumocystogram, inject 4 to 10 mL/kg of carbon dioxide or nitrous oxide while palpating the bladder, and stop when you feel back-pressure on the syringe or gas leaks around the catheter. For a double-contrast cystogram, remove urine, instill 2 to 5 mL of iodinated agent, roll the patient to coat the wall, then distend with gas.1 Palpate the bladder while filling it, because overdistension can rupture it.1
Myelography
A myelogram outlines the spinal cord by injecting contrast into the subarachnoid space. It has largely been replaced by CT and MRI where they are available. Use a nonionic iodinated agent (iohexol, iopamidol or iotrolan) at 180 to 240 mg/mL, ideally warmed to body temperature. The lumbar route (ideally L5-6, avoiding L4-5) is safer than a cerebellomedullary cistern injection. The dose is 0.3 to 0.45 mL/kg, and the total should not exceed 8 mL whatever the dog's size. Take lateral and VD views, with obliques as needed.4
Seizures after myelography were reported in 21.4% of dogs in one study and 3% in another. The difference was linked to the total volume given. The seizure risk was seven times higher with cisternal injections. Patients should be monitored in an ICU for at least 12 hours afterward.4
| Study | Agent and dose | Preparation | Avoid or modify when |
|---|---|---|---|
| Esophagram | Barium 2 to 5 mL/kg, paste-like | 12 h fast; remove leashes from neck; survey thorax | Suspected esophageal perforation (use iodinated) |
| Upper GI series | Barium about 10 mL/kg | 18 to 24 h fast; enema if colon full; survey abdomen | Suspected perforation; possible lower bowel obstruction |
| Barium enema | Barium 15% to 20% w/v, 20 to 30 mL/kg; air 2 mL/kg | Liquid diet 24 h; cleansing enemas, none irritating within 12 h | Suspected colon perforation or obstruction |
| Excretory urogram | Iodinated compound 850 mg/kg IV push | 12 to 18 h fast; enema; empty bladder; IV catheter | Watch for hypotension and anaphylaxis |
| Urethrogram | Iodinated, diluted, 5 to 10 mL | Enema; sedation or anesthesia as needed | Do not overfill the bladder against an occluding balloon |
| Pneumocystogram | CO2 or nitrous oxide 4 to 10 mL/kg | Urinary catheter; empty bladder | Severe or persistent hematuria (air embolism) |
| Myelogram | Nonionic iodinated 0.3 to 0.45 mL/kg, max 8 mL | General anesthesia; lumbar (L5-6) preferred | Monitor 12 h or more for seizures |
Sources: Kirk and Bistner's Handbook (ref 1); da Costa and others 2020 (ref 4).
Flowchart: choosing the agent
Species differences
- Dog: most published timings for the upper GI series are canine. Dogs get a second enema 3 to 5 hours before a GI series.1 For a urethrogram in a male dog, lidocaine (1 to 2 mL) can be injected into the urethra next to the balloon catheter.1
- Cat: for a urethrogram in a male cat, use a 4F balloon catheter or a 3.5F tomcat catheter inserted about 1.5 cm into the penile urethra. A voiding urethrogram (gentle pressure on the bladder) is needed to see the distal penile urethra.1 Cats and small dogs need smaller rectal catheters for a barium enema.1
- Horse: cervical myelography under general anesthesia carries real risk. In 278 horses, adverse reactions occurred in 34% and were linked to longer anesthesia time and higher contrast volume; neurologic reactions were the most common.7
Calculation
Worked example: myelogram volume with a cap. A 32 kg dog is scheduled for a lumbar myelogram. The protocol is iohexol 0.3 mL/kg, total no more than 8 mL.4
Volume = 32 kg x 0.3 mL/kg = 9.6 mL (kg cancels, leaving mL).
9.6 mL is more than the 8 mL maximum, so draw up 8 mL and confirm with the veterinarian. Larger volumes are used only if the first injection was not diagnostic.4
Second example: upper GI barium. A 12 kg dog at about 10 mL/kg: 12 kg x 10 mL/kg = 120 mL of barium suspension.1
Safety, legal and client education
- Before any barium study, ask: could this patient have a perforation? If yes, stop and confirm a water-soluble agent with the veterinarian.1
- Aspiration: barium studies should be postponed if severe aspiration pneumonia is present, because aspirated barium further harms lung function.3 Give oral contrast slowly and let the patient swallow.
- Pneumocystography is not harmless: fatal venous air emboli have occurred in dogs and cats, most often with severe hematuria. Use a gas that dissolves in blood, such as carbon dioxide or nitrous oxide, when you can.1
- Client points: explain the fast and the enemas, that the study may take several hours, and that barium may pass in the stool for 2 to 3 days.1 After a myelogram, explain why the pet stays in the hospital for monitoring.4

Common mistakes and exam traps
- Giving barium to a patient with suspected perforation. The correct choice is a water-soluble iodinated agent.1
- Skipping survey radiographs. They always come first.1
- Mixing up negative and double contrast. Negative is gas alone; double is a little positive agent plus gas.1
- Forgetting the 8 mL total cap on myelogram contrast in a large dog.4
- Thinking an IV urogram measures kidney function. It shows anatomy only.1
- Leaving a leash around the neck for an esophagram, or forgetting to label each film with the time after dosing.1
Memory aids
"Hole? No barium": if a hole (perforation) is suspected, barium is out and a water-soluble iodinated agent is used (memory aid).
Positive is white, negative is night: positive agents are radiopaque and look white; gas is radiolucent and looks black (memory aid).
A New Pet Cat: Arteriogram, Nephrogram, Pyelogram, Cystogram, the order of the excretory urogram phases (memory aid).
Eight is the gate: myelogram contrast is 0.3 to 0.45 mL/kg, but never more than 8 mL in total (memory aid).
15, 30, 90 to 120: duodenum, jejunum, ileocecal junction, the usual minutes for barium to arrive in a dog's upper GI series (memory aid).
Quick review
- Positive contrast is radiopaque; negative contrast is gas; double contrast uses both.
- Barium outlines the GI tract; iodinated agents are used IV, in the urinary tract and in the spinal canal.
- Suspected perforation: no barium, use a water-soluble iodinated agent.
- Avoid barium with possible lower bowel obstruction or severe aspiration pneumonia.
- Survey radiographs come before every contrast study.
- Esophagram: 12 h fast, leashes off the neck, barium 2 to 5 mL/kg, expose on the second swallow.
- Upper GI: 18 to 24 h fast, about 10 mL/kg barium, views at 0, 20 to 30 min, 1 h and 2 h.
- Barium enema: gravity only, bag no higher than 18 inches, 20 to 30 mL/kg.
- Excretory urogram phases: arteriogram, nephrogram, pyelogram, cystogram.
- Pneumocystogram: CO2 or nitrous oxide rather than room air; avoid with severe hematuria.
- Myelogram: nonionic agent, lumbar L5-6 preferred, 0.3 to 0.45 mL/kg, 8 mL maximum, monitor at least 12 h for seizures.
- IV iodinated agents can cause hypotension, anaphylaxis and kidney injury; nonionic agents are safer.